eQMS for Organ & Tissue Programs | Kintavo
SPECIALIZED THERAPIES & TISSUE PROGRAMS

Organ & Tissue

Tissue banks, transplant programs, and biorepository compliance — built for the chain of custody these programs demand.

AATB 21 CFR 1271 UNOS / OPTN
Book a demo for tissue programs ← All industries
THE PROBLEM

Every Graft Carries a Donor’s Record With It — Or Should.

Tissue banking spans recovery partners, processing, storage, and distribution — often across organizations, always across years. Donor eligibility files assemble from faxes and portals; processing records live in batch folders; distribution logs are spreadsheets. When a recall or adverse reaction demands the full chain, it is rebuilt by hand from all four.

The regulatory exposure runs both directions: FDA 1271 inspections sample donor files for completeness at the time of release, and AATB assessors trace grafts end to end. Both find the seams.

REGULATORY REQUIREMENTS

What AATB Standards and 21 CFR 1271 Require From Tissue Quality

Part 1271 requires donor eligibility determination — screening and testing documented before release — plus GTP processing controls, environmental monitoring, and tracking from donor to consignee. AATB standards deepen the requirements: qualified personnel, validated processes, controlled documents, and complaint and recall procedures that work. UNOS adds its own data and traceability duties for transplant programs.

Kintavo assembles the chain as work happens: eligibility files that show their completeness, processing under signature, and distribution linked donor-to-consignee for the recall you can then actually run.

WHAT AUDITORS LOOK FOR
Grafts released with donor eligibility documentation incomplete at release time.
Processing steps signed after the fact, in batches.
Distribution records that cannot trace a graft to its consignee within hours.
Recovery partner records in formats the quality system never reconciled.
WHAT KINTAVO REPLACES
Donor files from faxes and portals → Eligibility records with completeness enforced at release
Processing in batch folders → Step-signed processing records per graft
Distribution in spreadsheets → Donor-to-consignee tracking, query-ready
Recall records rebuilt by hand → Donor and graft records linked as created
Partner records unreconciled → Recovery documentation in the same system
CORE CAPABILITIES

From Recovery to Consignee. One Chain.

Donor Eligibility Records
Screening, testing, and physical assessment assembled per donor — with release blocked until the file is complete.
Processing Under Signature
Each processing step signed at completion, with environmental monitoring linked to the session.
Storage & Custody
Location, temperature events, and custody transfers on the graft record.
Distribution Records
Graft distribution documented with consignee records — the foundation for recall and adverse-reaction response.
Complaint & Recall Workflow
Structured intake, linked donor and graft records, consignee notification tracking, and FDA reporting timelines.
Partner Document Management
Recovery partner records received, verified, and attached to the donor file — one format, one system.
WHAT IT LOOKS LIKE IN PRACTICE

An adverse reaction report arrives naming a graft. The quality manager opens the donor record: the linked grafts and their distribution records are attached, storage inventory quarantines from the event, and consignee notifications are tracked to acknowledgment. The FDA report drafts from the record inside the deadline.

EVIDENCE, NOT CLAIMS

The Donor File That Proves Its Own Completeness.

Every eligibility element shows present, verified, and by whom — and release is gated on the set. When FDA samples files, completeness is a property the system enforced, not a hope the auditor tests.
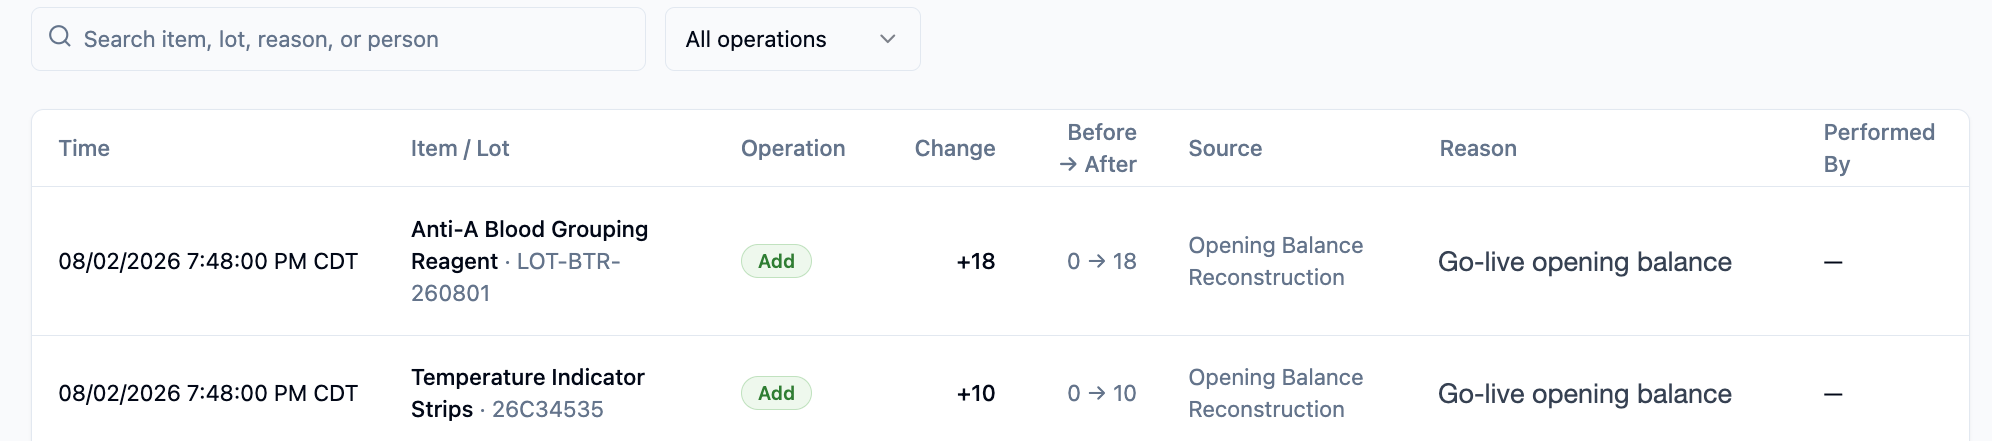
Timestamped, signed record rows — completeness enforced by the workflow that created them
SHOWN WITH SAMPLE DATA. YOUR NUMBERS APPEAR THE DAY YOU CONNECT YOUR SYSTEM.

Configured for your rules from day one.

CUSTODY
Chain of custody, provable
Recovery to release, every movement and condition logged against the donor record.
AATB
AATB & 21 CFR 1271
Standards mapping for tissue banks with the environmental and storage monitoring records inspectors expect.
STORAGE
Storage & equipment watch
Freezers, alarms, and calibrations in one lifecycle view — no more missing chart-recorder paper.
“
"Kintavo is the perfect solution for a regional blood center because it grows with you. We can automate our daily quality control processes, improve efficiency, and reduce costs."
Hoxworth Blood Center University of Cincinnati
MOST USED BY TISSUE PROGRAMS TEAMS
Document Control → Equipment Management → Deviation Management → Audit Management → Training Management →
QUESTIONS & ANSWERS

Organ & Tissue FAQ

Can Kintavo block release on incomplete donor eligibility?
Yes — the eligibility file is a checklist with verification, and release workflows gate on its completeness. The 1271 sampling finding becomes structurally impossible.
How does Kintavo support a recall?
Donor, graft, and distribution records link as they are created, and the recall workflow tracks consignee notification to acknowledgment — so response starts from connected records, not a reconstruction.
Does Kintavo handle recovery partner documentation?
Yes — partner records are received into the donor file with verification steps, so the file is one chain regardless of how many organizations touched it.
Does Kintavo support AATB accreditation?
The standards AATB assesses — personnel, process control, documents, complaints, recalls — run as daily workflows generating live evidence for the assessment.

See Kintavo configured for tissue programs.

Bring your real pain points. We'll show you exactly how it solves them — in your regulatory language.

Book a Personalized Demo
RELATED Who runs on Kintavo → Hoxworth case study → Compare platforms → Pricing →